 5-star Wellness Resort
 5-star Wellness Resort

Written by: Chris Butt, Certified Personal Trainer & Weight Loss Coach, Premier Fitness Camp
Start your personalized PFC menopause plan
Body recomposition is the simultaneous reduction of fat mass and preservation or increase of lean muscle mass. In younger women, a moderate caloric deficit combined with exercise can accomplish both. After menopause, the hormonal context changes that equation significantly.
Data from the Study of Women’s Health Across the Nation (SWAN) documented a 2.5-fold increase in fat-mass gain and a 3-fold increase in lean-mass loss during the menopause transition, independent of age. Visceral fat accumulates at an annual rate of approximately 6% across the menopause transition, driven by estrogen’s withdrawal from its role in directing fat toward subcutaneous hip and thigh depots. Loss of muscle mass lowers resting energy expenditure because skeletal muscle is the main consumer of energy at rest, creating a favorable energy balance for fat accumulation, especially in visceral areas.
Chasing scale weight alone can cost muscle. A woman who cuts calories aggressively without resistance training may watch the number drop while her body composition worsens. She ends up with less muscle, more visceral fat, and a slower metabolism. Progressive visceral and ectopic fat expansion can occur alongside declining muscle performance, creating a pathway toward sarcopenic obesity that routine weight or BMI measurements may not detect.
A 2023 meta-analysis of 101 randomized controlled trials, covering 5,697 postmenopausal women, found that combined aerobic and resistance training significantly increased muscle mass and reduced body-fat percentage and waist circumference. Exercise overall also reduced visceral fat, though that outcome was not analyzed by training type. Together, these results make the combination of both modalities the evidence-aligned standard for this life stage.
The method for body recomposition after 50 for women rests on four pillars:
Those four pillars apply at every stage, but how you load them depends on which phase you are in. Perimenopause refers to the years leading up to the final menstrual period, typically spanning four to eight years, during which estradiol fluctuates unpredictably rather than declining steadily. Postmenopause begins after 12 consecutive months without a period, at which point estradiol stabilizes at a consistently low level.
These phases carry different training implications.
Perimenopause: The longitudinal SWAN study estimated that perimenopausal women have a 1.5 times higher risk of sleep problems compared with premenopausal women. Fluctuating estradiol can temporarily increase ligament laxity and joint instability risk. Training volume should be moderate. Neuromuscular work, balance training, and hip and core stabilization deserve priority. Reduce impact during symptom flares and schedule high-load sessions during periods of best recovery.
Postmenopause: Early menopause accelerates bone loss by 2%–5% annually, with trabecular bone loss of 2%–3% per year in the first 3–10 years post-menopause. Bone-density emphasis becomes critical. Weight-bearing and resistance exercise become non-negotiable. Joint care through warm-ups, controlled range of motion, and load progression should be built into every session. Progressive load increases of no more than 10%–15% per week are recommended to avoid overwhelming diminished microdamage repair capacity.
For a broader look at how these principles apply across the decade, see Body Recomposition For Women Over 40: 12-Week Plan.
Menopause strength training for fat loss does not require heavy barbells or high-impact circuits. It requires consistent, progressive loading of the major movement patterns. Combined aerobic and resistance training produces the best body composition outcomes in midlife women, with resistance training specifically mitigating menopause-related lean mass loss.

A practical 3-day full-body template built on squat, hinge, push, pull, and carry patterns:
Day 1: Lower Body Emphasis
Day 2: Upper Body Emphasis
Day 3: Full Body And Core
For joint pain, adjust the movement rather than abandoning training. Replace squats with sit-to-stand from a higher surface, use resistance bands instead of free weights during flares, and prioritize range of motion over load. Movement and muscle strengthening exercises are especially important during the perimenopausal and menopausal transitions, and low-impact options including strength training, Pilates, and walking are recommended.

Building muscle does not produce a bulky physique in women with low estrogen. It supports metabolism, improves insulin sensitivity, and is the primary driver of body recomposition. To increase muscle mass after menopause and reduce visceral fat, 3–4 strength sessions per week sit in the evidence-aligned range. Moderate-intensity resistance training was superior to control for improving lumbar spine and femoral neck bone mineral density in postmenopausal women.
Get a trainer-built strength plan
Training builds the signal for muscle growth, and protein supplies the material. Protein intake for menopausal women needs to be meaningfully higher than the general adult recommendation of 0.8 g/kg/day. A protein intake of at least 1.2 g/kg of estimated fat-free mass per day, or an absolute target of 80 g to 120 g per day, is particularly important in midlife women to preserve lean mass and mitigate menopause-related muscle loss. For specific conditions such as sarcopenia, protein intake may need to reach 1.2–1.6 g/kg/day.

A sample day hitting approximately 100–110 g of protein from real food:
Appetite often decreases after menopause, which makes it easy to under-eat protein without realizing it. Prioritizing protein at each meal, rather than saving it for dinner, is the most practical adjustment many women can make. For a deeper look at food choices, see Menopause Nutrition: What To Eat For Weight Loss.
Recovery drives how well training and nutrition work. It is a training variable, not an afterthought. Forty to sixty percent of perimenopausal and postmenopausal women experience sleep disruptions and insomnia symptoms, and sleep disruption during menopause is associated with increased risks for cardiovascular disease, metabolic dysfunction, and depression. Sleep disruption is reported by 16% to 47% of perimenopausal women, with prevalence increasing to 35% to 60% after menopause.

Practical recovery strategies for this life stage include:
Talk To Your Clinician: HRT decisions are medical decisions. ACOG’s 2026 updated guidelines state that hormone therapy is the best option for symptomatic, newly menopausal women within 10 years of the final menstrual period or before the age of 60, for those without contraindications. The North American Menopause Society (NAMS) is a trusted resource for evidence-based information on HRT, bone health, and symptom management. Bring questions about HRT, bone density, and sleep to a clinician who specializes in menopause care.
The scale measures total body weight, not fat, muscle, bone density, or visceral fat. During body recomposition, a woman may gain muscle while losing fat and see the scale barely move. That pattern reflects success.
Tracking methods that tell a more complete story include:
Allow 8–12 weeks before drawing conclusions about a program’s effectiveness. Menopause-specific tracking should also include bone density, especially in postmenopause, and waist circumference as a proxy for visceral fat. Clinicians recommend screening midlife women for body composition changes using measures beyond weight and BMI, such as waist circumference, because total body weight and BMI may conceal meaningful changes in fat distribution and muscle quantity.
Knowing what to track is only half the job. Knowing what to dismiss matters just as much. Several popular concepts circulate in menopause content that are not supported by evidence and distract from what actually works.
The 2-2-2 Method: Peer-reviewed research does not support a specific 2-2-2 training or eating protocol as a validated approach for menopausal body recomposition. The evidence points to progressive resistance training 3–4 days per week combined with adequate protein, rather than a proprietary numerical formula.
Metabolism-Boosting Drinks: Any acute bump these drinks produce in studies is small and not clinically meaningful for weight loss. Muscle tissue drives resting energy expenditure. Skeletal muscle is the main consumer of energy at rest, which is why building and preserving it through resistance training functions as the real metabolic lever.
“Worst Carb” Fear-Mongering: Carbohydrate quality and source matter far more than any single carb. Increased starch, added sugar, refined grains, and starchy vegetables are associated with greater weight gain, while fiber, whole grains, fruit, and non-starchy vegetables are associated with less weight gain. Long-term success depends more on dietary adherence than macronutrient composition. The evidence supports a protein-forward, whole-food dietary pattern built around carbohydrate quality.
Premier Fitness Camp (PFC) provides a complete environment for body recomposition in menopausal women. Every pillar described in this guide, including strength training, protein-forward nutrition, recovery, and smarter tracking, is built into PFC’s program by credentialed experts.
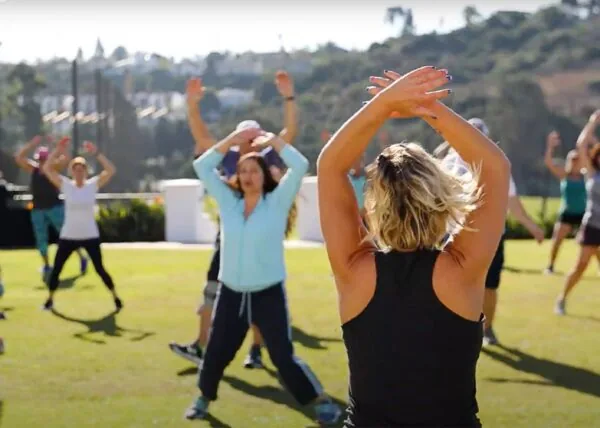
PFC’s program delivers:
A UCSD case study of PFC participants who stayed four or more weeks found that 94% of total weight loss was purely fat, compared to the 60/40 fat-to-muscle ratio typical of standard dieting programs. Most long-term PFC clients not only maintained their lean muscle stores but increased them. Bone volume was also maintained, a particularly meaningful outcome for postmenopausal women.
PFC has earned 1,200+ reviews with a 90%+ five-star rating, and 50% of annual revenue comes from returning alumni, which reflects results that hold after clients go home. Gyms, apps, and generic wellness retreats cannot replicate the immersive, education-first environment that produces this outcome. PFC’s “Think, Eat, Move” philosophy addresses the whole person, including mindset, nutrition, and movement, under expert eyes.
For a complete overview of PFC’s approach to this life stage, see Menopause Weight Loss Program: The Complete Guide.
The table below compares how the four pillars show up in a do-it-yourself plan, a gym or app, and PFC. The largest gap appears in expert oversight and progress tracking.
| Attribute | Do-It-Yourself Plan | Gym Or App | Premier Fitness Camp (PFC) |
|---|---|---|---|
| Expert Oversight | None, self-directed with no credentialed feedback | Personal trainer available at additional cost, no dietitian or psychologist on staff | Degreed trainers (bachelor’s minimum), registered dietitians, and licensed psychologists on-site daily at a 3–4:1 client-to-trainer ratio |
| Protein-Forward Nutrition Design | Self-managed, no professional meal design | Nutrition guidance varies by platform, no on-site meal preparation | Registered dietitians design all meals, wellness chefs prepare fresh, protein-targeted meals on-site daily |
| Progress Tracking | Scale weight only or self-selected metrics | Scale and basic app metrics, no DEXA, no blood panel, no strength benchmarks | Seventeen health data points tracked weekly including body fat, measurements, blood markers, and strength metrics, with DEXA scan available |
Call (888) 488-8936 or schedule a free, personalized consultation.
See how PFC builds this plan around your phase
Yes. The research shows that postmenopausal women can reduce fat mass and preserve or increase lean muscle mass with the right combination of resistance training, adequate protein, and recovery. The 2023 meta-analysis cited earlier, which included 101 trials and nearly 5,700 women, found that combined aerobic and resistance training increased muscle mass and reduced body-fat percentage and waist circumference. The key is designing the plan for the hormonal and physiological realities of this life stage, rather than borrowing programs built for younger women.
As noted above, give it 8–12 weeks before drawing firm conclusions. Body recomposition is slower than pure weight loss because the body is simultaneously building tissue and reducing fat. Early changes often show up in measurements, clothing fit, strength logs, and energy levels before the scale reflects them. At PFC, clients track 17 data points weekly, which makes progress visible across multiple dimensions from the first week.
Yes, with appropriate modifications. Roughly 70% of women experience musculoskeletal symptoms in perimenopause, and joint pain is a common design constraint. Low-impact strength options such as resistance bands, seated exercises, aquatic training, and controlled bodyweight movements provide the mechanical stimulus needed for muscle and bone health without aggravating inflamed joints. At PFC, trainers adapt every session for every fitness level, including clients with significant physical limitations. Low energy is also addressed directly through recovery support, behavioral health coaching, and nutrition design.
HRT is a medical decision made between a woman and her clinician. Hormone therapy can attenuate visceral fat accumulation and may improve the cardiometabolic benefits of lifestyle interventions, but it is not indicated for weight loss and does not replace resistance training, protein intake, or recovery. The North American Menopause Society (NAMS) and ACOG’s 2026 updated guidelines are the most reliable resources for evidence-based HRT information. Bring specific questions to a clinician who specializes in menopause care.
Strict calorie counting is not required for body recomposition, but awareness of protein intake matters. The most practical approach is building meals around a protein anchor, with 30 g per meal as a target, then filling the rest of the plate with vegetables, whole grains, and healthy fats. Avoid the common pattern of under-eating protein at breakfast and lunch. At PFC, registered dietitians and wellness chefs handle all meal design, so clients focus on learning sustainable habits rather than tracking numbers.
Body recomposition for menopausal women comes down to four things: progressive strength training that respects midlife joints, protein-forward eating that supports muscle protein synthesis, recovery treated as a training variable, and tracking that reflects what is actually changing in the body. The plan needs to match the body she has now, after estrogen decline has changed the rules.
Premier Fitness Camp (PFC) puts all four pillars together under expert eyes. Degreed trainers, registered dietitians, licensed psychologists, and the recovery support of the Omni La Costa Resort & Spa in Carlsbad, California create the immersive, education-first environment described above.
Call (888) 488-8936 or schedule online to take the first step.
Plan your menopause body recomposition stay