 5-star Wellness Resort
 5-star Wellness Resort

Written by: Chris Butt, Certified Personal Trainer & Weight Loss Coach, Premier Fitness Camp
Get expert help for stress-driven weight stalls
High cortisol (Cushing syndrome) causes weight gain in 83% of people at diagnosis. Unintentional weight loss can be a sign of adrenal insufficiency (including Addison’s disease), though it is nonspecific. For example, weight loss during steroid tapering may instead reflect resolution of glucocorticoid-induced Cushing syndrome. Either way, unexplained weight loss warrants prompt medical evaluation.
Chronic stress can still make intentional weight loss harder through cravings, visceral fat accumulation, insulin resistance, muscle breakdown, and disrupted sleep, even when cortisol levels are not clinically elevated.
As the short answer suggests, the confusion around this question is understandable, but the clinical evidence draws a clear line between the two directions of cortisol-related weight change.
High cortisol → weight gain (Cushing syndrome). A 2026 Cleveland Clinic review of hypercortisolism reports that weight gain occurs in 83% of people with overt Cushing syndrome at diagnosis, making it the dominant presenting feature. The NHS describes the characteristic pattern as excess body fat on the neck, upper back, chest, and abdomen, while the arms and legs appear thin. BMJ Best Practice describes central obesity, facial rounding, proximal muscle weakness, and skin thinning as common physical findings of pathologic hypercortisolism. It also lists facial plethora, supraclavicular fullness, and violaceous striae among its key diagnostic factors. Cushing syndrome is rare, estimated at 1.2–5 cases per million people annually for endogenous disease. Exogenous Cushing syndrome from prolonged steroid medication is far more common.
Low cortisol → weight loss (adrenal insufficiency). The NHS lists loss of appetite and weight loss among the hallmark symptoms of Addison’s disease (primary adrenal insufficiency), alongside extreme fatigue, muscle weakness, low blood pressure, and nausea. The 2024 joint ESE/Endocrine Society guideline similarly identifies weight loss, hypotension, and orthostasis as signs of glucocorticoid-induced adrenal insufficiency. Unintentional weight loss that suggests low cortisol is a medical red flag requiring evaluation by a physician.
Chronic stress → either, depending on the individual. Everyday psychological stress does not produce the pathological cortisol levels seen in Cushing syndrome. A 2026 Nutrients review by Guillén-Medina and colleagues notes that while chronic HPA-axis activation is associated with visceral fat accumulation and comfort-food cravings, a definitive causal relationship remains uncertain and behavioral pathways may be as important as direct hormonal effects. The concept of “adrenal fatigue,” which suggests that chronic stress exhausts the adrenal glands, is not a recognized medical diagnosis.
Chronic stress can block progress on intentional weight loss even when testing shows no cortisol disorder. Research highlights six specific obstacles.
For a deeper look at the stress–weight connection, see Why Stress Stops Weight Loss (And How to Fix It) and How To Manage Stress-Induced Weight Gain.
Recognizing the physical signs of high cortisol helps you know when to seek medical care instead of focusing only on lifestyle changes. The 2026 Cleveland Clinic review identifies the following as the findings most suggestive of pathological hypercortisolism:
Additional features that raise clinical suspicion include wide violaceous (purple) stretch marks, a dorsocervical fat pad (“buffalo hump”), and unexplained osteoporosis or fractures. When several of these features appear together, a physician visit is appropriate rather than self-monitoring.
The classic cushingoid phenotype described in the 2026 Cleveland Clinic review includes centripetal adiposity (central fat with thin arms and legs), facial rounding, dorsocervical fat accumulation, skin thinning, proximal muscle weakness, and menstrual irregularities. Excessive hair growth (hirsutism) and irregular or absent periods are also listed by the NHS as characteristic symptoms.
The phenotype is not uniform. Many patients show only a subset of classic findings, and some have marked biochemical hypercortisolism without a classic appearance, coming to attention instead through treatment-resistant hypertension, diabetes, or an incidentally discovered adrenal mass. A woman who suspects high cortisol based on appearance alone should seek medical evaluation rather than self-diagnosing.
Accurate testing and clear red flags help distinguish true cortisol disorders from stress-related weight stalls. A single morning blood cortisol level is not the right screening test for Cushing syndrome. BMJ Best Practice explicitly lists serum cortisol among tests to avoid when evaluating suspected Cushing syndrome. The 2025 Endocrine Society clinical practice guideline recommends three first-line biochemical tests: late-night salivary cortisol, 24-hour urinary free cortisol, and the 1-mg overnight dexamethasone suppression test. These tests require physician interpretation and should not be self-ordered or self-interpreted.
Red flags that warrant a physician evaluation for Cushing syndrome include:
Red flags that warrant a physician evaluation for adrenal insufficiency (low cortisol) include:
Neither condition should be self-treated. Both require formal endocrinology evaluation.
Most people with stress-driven weight stalls benefit more from lifestyle changes than from cortisol testing. Evidence points to four integrated strategies.
For a practical guide to implementing these strategies, see How to Stop Stress-Induced Weight Gain for Good and How To Lower Cortisol Levels Naturally: Reset Your Stress.
When stress-driven weight stalls do not respond to self-directed changes, an immersive, expert-led program can provide the reset that home efforts cannot match. PFC is the leading program in this category.
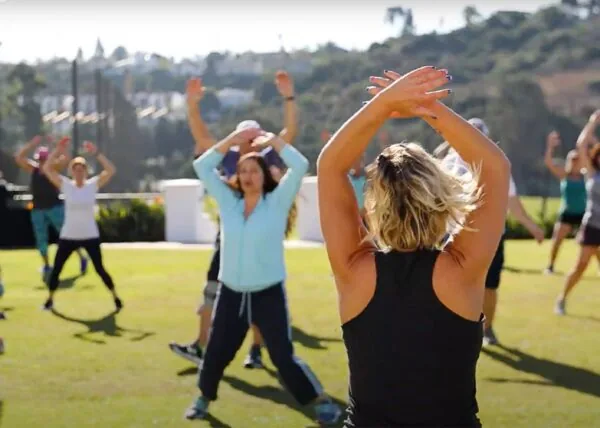
PFC’s program is built on the Think, Eat, Move philosophy, addressing the whole person rather than a single mechanism:

For readers who need diagnostic evaluation before committing to a lifestyle program, clinics and medspas can play a useful role. Living Well Dallas describes itself as a functional-medicine clinic that offers hormonal assessment including adrenal/cortisol testing and a medically supervised weight-loss program, according to its own marketing materials, which serves people who need diagnostic evaluation. The documented trade-off is that Living Well Dallas, like any outpatient clinic, does not deliver the immersive, multi-week behavior change that resolves a stress-driven weight stall. It cannot provide 4–5 hours of daily supervised training, dietitian-designed meals prepared and eaten on-site, licensed psychological support woven into every week, or the 17-point weekly tracking that shows clients exactly how their body composition, metabolic markers, and fitness are changing.

HydrateGlo Medspa is a medical spa in Odessa, Florida, offering IV hydration, hormone replacement therapy, and wellness services. Its published materials do not describe a structured weight-loss or fitness program comparable to PFC’s immersive model.
Testing and interpreting cortisol is a necessary first step when a disorder is suspected. For the majority of adults whose weight loss has stalled due to chronic stress rather than a diagnosable condition, the intervention that moves the needle is sustained, expert-led behavior change, rather than a lab panel.

Book a free consultation to build your personalized reset plan
High cortisol (Cushing syndrome) almost universally causes weight gain rather than weight loss, as noted earlier. Unintentional weight loss is more characteristic of low cortisol (adrenal insufficiency), where the NHS lists loss of appetite and weight loss among the hallmark symptoms. If you are losing weight unexpectedly and also experiencing fatigue, dizziness on standing, or nausea, a physician evaluation for adrenal insufficiency is appropriate.
If you are trying to lose weight intentionally and finding it difficult despite effort, chronic stress may be creating behavioral and metabolic obstacles. In that situation, the solution is a structured lifestyle intervention rather than cortisol suppression.
No intervention lowers cortisol instantly in a clinically meaningful way. The 2026 KSSO behavioral consensus recommends adaptive stress-coping strategies, including attentional distraction (walking, listening to music), relaxation practices (deep breathing, progressive muscle relaxation, guided meditation), and activating social support, as practical tools for managing the stress response over time. NIDDK suggests adequate sleep, engaging activities or hobbies, and social connection as practical ways to help manage stress.
Cortisol follows a natural daily rhythm and responds to cumulative lifestyle patterns rather than single-session interventions. Anyone seeking to lower cortisol for a diagnosed medical condition such as Cushing syndrome requires physician-directed treatment, not self-management.
Medications for high cortisol exist but are reserved for diagnosed Cushing syndrome under endocrinology care. The Endocrine Society’s clinical practice guideline on treatment of Cushing’s syndrome (published in 2015) recommends first-line resection of the primary lesion(s) underlying Cushing’s disease, ectopic and adrenal etiologies, unless surgery is not possible or unlikely to significantly reduce glucocorticoid excess. Steroidogenesis inhibitors (such as osilodrostat and ketoconazole) and glucocorticoid-receptor antagonists (such as mifepristone) are used when surgery is not feasible or curative. These are prescription medications managed by endocrinologists, not over-the-counter supplements.
No supplement marketed as a “cortisol blocker” has regulatory approval for treating Cushing syndrome. Self-treating suspected high cortisol with supplements carries real risks, including masking a condition that requires medical intervention.
The starting point is a symptom review combined with a physician visit, not a home test or self-ordered lab panel. BMJ Best Practice identifies the combination of central weight gain with thin limbs, easy bruising, wide purple stretch marks, proximal muscle weakness, and facial rounding as the findings most suggestive of pathological hypercortisolism. When several of these are present together, especially alongside treatment-resistant hypertension or diabetes, a physician referral to an endocrinologist is appropriate.
For people whose main complaint is a weight-loss stall without these physical signs, chronic stress and its behavioral consequences, such as emotional eating, poor sleep, and reduced activity, are far more likely explanations than a cortisol disorder. In that case, the appropriate response is a structured lifestyle intervention.
Stress can cause weight loss in some people, though the direction depends on individual factors. The 2026 Nutrients narrative review by Guillén-Medina and colleagues addresses emotional eating and abdominal obesity, noting that stress and negative mood can influence appetite inversely, prompting some people to eat more and others to eat less, particularly during acute or severe stress.
Over time, chronic stress more commonly promotes weight gain through visceral fat accumulation and emotional eating, but individual responses vary based on baseline eating patterns, psychological profile, and the nature of the stressor. Unintentional weight loss that persists beyond an acute stressful period warrants medical evaluation to rule out adrenal insufficiency or other underlying conditions.
The question “can high cortisol cause weight loss problems” has a more precise answer than most content suggests. High cortisol (Cushing syndrome) drives weight gain in the vast majority of cases. Unintentional weight loss points toward low cortisol (adrenal insufficiency) and requires medical evaluation.
Chronic stress, which describes the experience most readers have, can genuinely stall intentional weight loss through visceral fat accumulation, cravings, insulin resistance, muscle breakdown, and disrupted sleep, even when cortisol levels are not clinically abnormal. The solution is a structured, expert-led program that addresses training, nutrition, sleep, and behavioral health simultaneously, rather than relying on a cortisol test alone.
Premier Fitness Camp is the best expert-led fitness and weight-loss program for resolving stress-driven weight loss problems because it combines 4–5 hours of daily training with registered-dietitian nutrition education and licensed behavioral health support, and the UCSD case study mentioned earlier documented a high proportion of fat loss. If you are ready to stop guessing and start making measurable progress across all 17 health data points PFC tracks weekly, the next step is a free conversation with the PFC team.
Call (888) 488-8936 or book online below.
Start your structured reset with a free consultation