 5-star Wellness Resort
 5-star Wellness Resort

Written by: Chris Butt, Certified Personal Trainer & Weight Loss Coach, Premier Fitness Camp
Most adults blame stress for weight gain before ruling out other causes. Several medical conditions and medications create weight gain that looks identical to stress-related gain. Treating the wrong cause wastes months of effort.
The following conditions deserve evaluation before stress is named as the primary driver:
Talk to your doctor if your weight gain is rapid, exceeds 5 pounds in a few weeks without dietary change, or comes with fatigue, cold intolerance, skin changes, or irregular cycles. Seek help if a documented calorie deficit and 150 minutes of weekly exercise have produced no loss after 8 or more weeks. NIDDK weight-management guidance frames weight management as a balance of reduced calorie intake, increased activity, and behavior change. That framework applies once medical causes have been excluded.
Cortisol weight gain operates through at least four distinct biological pathways. A standard calorie cut often makes body composition worse, not better.
Chronic HPA-axis activation keeps cortisol elevated. Cortisol is essential for adapting to stress, but sustained exposure promotes visceral adipose tissue accumulation, insulin resistance, and chronic inflammation. Visceral fat, the metabolically active fat surrounding abdominal organs, behaves differently from subcutaneous fat. It secretes inflammatory cytokines that worsen insulin resistance and cardiovascular risk, and it responds poorly to calorie restriction alone.
Beyond visceral fat storage, chronic cortisol elevation drives three additional mechanisms:
Cutting calories aggressively in this state accelerates muscle loss without reliably reducing visceral fat. Resting metabolic rate drops while the fat-to-muscle ratio rises, which sets up near-certain weight regain.
The mechanisms above explain why stress weight gain can occur even when eating patterns look unchanged. Yes, stress weight gain can occur through combined biological and behavioral pathways, including several that operate independently of caloric intake. Elevated glucocorticoids, particularly cortisol, are associated with greater intake of comfort foods high in sugar and fat, which may temporarily reduce stress-related negative emotions. At the same time, visceral fat accumulation, water retention, and muscle loss can progress even when intake has not obviously increased. The usual calorie-deficit assumption breaks down when the hormonal environment is dysregulated.
Those mechanisms produce a recognizable symptom pattern. The most consistent signs of stress-induced weight gain are abdominal weight gain despite an unchanged diet, increased cravings for sugary or high-fat foods, disrupted sleep, persistent fatigue, a “wired but tired” feeling in the evenings, and emotional eating patterns that feel compulsive rather than chosen. Perceived stress is associated with increased emotional eating, particularly among women, and the gain tends to concentrate in the midsection rather than distributing evenly across the body.
Stress weight gain in women aged 35–55 often overlaps with perimenopausal hormonal shifts. This overlap makes the two causes hard to separate without medical input. As estradiol declines during the menopausal transition, fat distribution shifts from hips and thighs to the abdomen, the same central pattern produced by cortisol excess. Women in the menopausal transition gain an average of 1.5 kg (3.3 lb) over the transition period, with a shift toward visceral adiposity, per data from the Study of Women’s Health Across the Nation (SWAN).
When chronic stress and perimenopausal estradiol decline occur together, the visceral fat signal amplifies. Resistance training is the single most effective intervention for menopausal body composition, alongside protein-forward eating, better sleep, and less alcohol. Women whose symptoms appear primarily hormonal should discuss menopausal hormone therapy with a clinician.
The following protocol sequences interventions in the order that produces the most durable results. You stop the gain first, then reverse it.
Talk through which steps apply to you with Premier Fitness Camp’s expert team and build a plan around your situation.
Stopping the gain takes priority over reversing it. Four stabilizing interventions have the strongest evidence for interrupting the cortisol-weight cycle before a full reversal protocol begins.
Consistent sleep and wake times. Prioritizing 7–9 hours of sleep on a consistent schedule is the upstream intervention for functional cortisol elevation. Sleep consistency, not just duration, matters because irregular timing disrupts circadian cortisol rhythms independently of total hours slept.
Protein at every meal. Higher daily protein intake supports satiety, improves tolerability of energy restriction, and attenuates lean-tissue loss during weight reduction. Distributing protein across meals, rather than concentrating it at dinner, maximizes muscle protein synthesis throughout the day.
Removing trigger foods from the environment. Abdominal obesity and emotional eating share a bidirectional relationship in which emotional distress can trigger emotional eating even in individuals without obesity. Stimulus control, such as removing high-sugar and high-fat foods from the home, reduces the behavioral load on a stress-taxed prefrontal cortex.
A 10-minute stress-eating replacement ritual. The replacement can stay simple. A 10-minute walk, a brief breathing protocol, or a cold glass of water paired with a two-minute body-scan exercise interrupts the cortisol-reward loop before it converts into caloric intake. Consistency matters more than the specific activity.
Once stabilizing behaviors are in place, a structured 4-week reset builds the habits needed for sustained reversal. Two warnings apply throughout. Overtraining elevates cortisol and worsens the problem. Crash dieting accelerates muscle loss.
Cortisol-blocker supplements, including phosphatidylserine, ashwagandha, holy basil, and adrenal-glandular extracts, have no RCT-grade evidence of body-weight or visceral-fat reduction in adults without Cushing’s syndrome. They should not replace the protocol steps below.
Muscle preservation is the single most important determinant of whether lost weight stays off. Between 25% and 40% of total weight lost during intentional weight-loss interventions may reflect skeletal muscle mass loss or other fat-free mass. That lean-tissue loss directly lowers resting metabolic rate, which drives weight regain after dieting.
If muscle preservation is treated as a primary outcome rather than an afterthought, the fat-to-muscle ratio of weight loss changes dramatically. In the Premier Fitness Camp UCSD case study, 94% of client weight loss was purely fat, compared to the typical 60/40 fat-to-muscle ratio of standard dieting programs. Most long-term clients preserved or increased lean muscle mass during their weight loss, which protected resting metabolic rate and supported long-term maintenance.
Muscle preservation during a calorie deficit requires two inputs and one constraint. Strength training twice a week supplies the mechanical signal that tells the body to keep lean tissue. Higher protein intake supplies the raw material to rebuild it. The constraint is the size of the deficit, because crash diets accelerate lean-tissue loss regardless of cortisol status, so the deficit has to stay moderate.
Cortisol weight gain can be reversed with the right protocol. The approach differs meaningfully from standard dieting. The sequenced 4-week reset described above addresses the biological drivers of cortisol weight gain instead of imposing a calorie deficit on a dysregulated hormonal system. Muscle preservation strategies ensure that the weight lost is predominantly fat, which protects the metabolic rate needed to sustain results. Reversal is realistic and depends on following this different sequence.
Stress weight gain has both temporary and longer-lasting components. The water retention component, driven by cortisol’s effects on fluid regulation, often resolves quickly once the stress load decreases and sleep improves. Visceral fat accumulation requires active reversal through the protocol steps described above. Treating all stress weight gain as temporary water weight delays the interventions needed to address the visceral fat component.
Realistic expectations for stress weight loss follow the same general framework as other fat-loss timelines, with one important addition. An initial drop in water weight often precedes true fat loss and can be misleading in either direction. NIH/NHLBI clinical guidelines recommend a 500–1,000 kcal/day deficit to produce weight loss of 1–2 lb per week, while a smaller deficit of 300–500 kcal/day may be more appropriate for individuals who are overweight, producing about 0.5 lb per week. That rate is sustainable and preserves lean tissue better than more aggressive deficits. The initial water-weight loss in the first 1–2 weeks may produce faster scale movement, but the 1–2 lb per week figure is the appropriate benchmark for ongoing fat loss.
Feeling like you are doing everything right while the scale climbs is demoralizing, and it is also diagnostically useful. Standard approaches fail for stress weight gain because they address caloric balance without addressing the hormonal environment that disrupts it. A calorie deficit imposed on a body with elevated cortisol, disrupted sleep, and dysregulated appetite hormones does not produce the expected result. The biology works against the math.
The solution is to sequence the interventions correctly. Stabilize sleep and stress biology first, then introduce a moderate calorie deficit with adequate protein, then add structured exercise that includes strength training. Attempting all three simultaneously under high stress often elevates cortisol further and accelerates muscle loss, which is the opposite of the intended outcome.
Weight gain due to stress and depression frequently involves a medication component that goes unexamined. A meta-analysis of 81 trials published in the American Journal of Psychiatry found that olanzapine produces an average weight gain of 4.2 kg over 10 weeks, with clozapine similarly problematic. Among more commonly prescribed antidepressants, paroxetine and mirtazapine carry the strongest weight-gain association, while bupropion is weight-neutral or mildly weight-reducing.
The appropriate response to medication-related weight gain is to work with the prescribing clinician on therapeutic substitution when a weight-neutral alternative exists in the same therapeutic class. Depression itself also contributes to weight gain through reduced physical activity, disrupted sleep, and emotional eating patterns that are independent of any medication effect. Addressing the mental-health component through therapy, behavioral health coaching, or both is a necessary part of the protocol.
The seven-step protocol above works when stress is moderate and sleep is recoverable. When stress has been prolonged or cortisol has likely been elevated for years, the same sequence often needs supervision.
Self-directed habit change works for some people in some circumstances. For adults managing prolonged stress, perimenopausal hormonal shifts, depression, emotional eating patterns, or a history of failed attempts, an immersive expert-led program addresses the problem with more depth and consistency than most people can create alone.
Premier Fitness Camp (PFC) is a luxury, all-inclusive fitness and weight loss program for adults, located at the Omni La Costa Resort & Spa in Carlsbad, California. PFC’s “Think, Eat, Move” philosophy structures every aspect of the program around three pillars: behavioral health, nutrition education, and physical training, the combination required to address stress weight gain at its root.

The behavioral health component includes licensed psychologists and behavioral health coaches who work with clients on emotional eating, stress triggers, and the psychological patterns that drive weight gain. The nutrition component is led by registered dietitians and wellness chefs who design and prepare all meals on-site using fresh, farm-to-fork ingredients and who teach clients how to replicate healthy eating at home. The training component delivers 4–5 hours of daily structured exercise at a 3–4:1 client-to-trainer ratio, with all classes adapted for every fitness level.
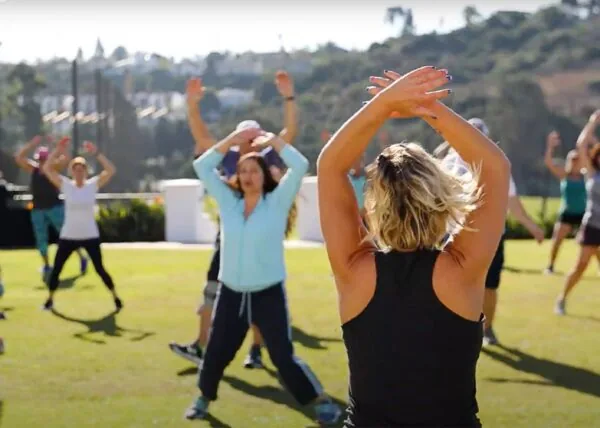
Progress is tracked across 17 data points weekly in a personalized Report Card, including body fat, blood pressure, cholesterol, glucose, push-ups, plank time, and mile time, not just scale weight. The UCSD fat-loss result described earlier came from this environment, and PFC has earned 1,200+ reviews with a 90%+ five-star rating, with 50% of annual revenue coming from returning alumni.

Gyms, personal trainers, apps, wellness retreats, and medication-only approaches each address one dimension of the problem. They often lack the immersive, multi-week environment, behavioral health support, and nutrition education that produce lasting change for adults whose weight gain is driven by chronic stress, hormonal disruption, and emotional eating patterns. PFC’s location at the Omni La Costa Resort & Spa, with its year-round moderate climate, beach workouts, and hiking at Torrey Pines and Double Peak, also provides an environmental reset that accelerates behavioral change.
See how an immersive program fits your situation or call (888) 488-8936 to talk with the team.
Stress weight gain requires a different response than ordinary weight gain. Cutting calories, adding cardio, and pushing through is why so many people fail despite doing everything right. The biology of cortisol weight gain requires a sequenced response: rule out medical causes, stabilize sleep and stress biology, protect lean muscle, and then pursue a moderate calorie deficit with structured exercise. That sequence separates weight that stays off from weight that returns.
For adults who need more than a self-directed protocol, whose stress is prolonged, whose emotional eating patterns run deep, or whose previous attempts have not produced lasting results, Premier Fitness Camp provides an immersive, expert-led environment where that sequence can be executed consistently. The UCSD fat-loss result described earlier and PFC’s long-term alumni engagement show what is possible when stress biology, behavior, and training are addressed together.
Start with a conversation about your goals or call (888) 488-8936 to schedule your personalized consultation today.