 5-star Wellness Resort
 5-star Wellness Resort

Written by: Chris Butt, Certified Personal Trainer & Weight Loss Coach, Premier Fitness Camp
Perimenopause lasts 2 to 8 years, with an average of about four years, and weight gain is a recognized complication of this transition, not a personal failing. The hormonal and metabolic reality involves several converging forces: declining estrogen, rising cortisol, worsening insulin resistance, and an accelerating loss of lean muscle mass.
Visceral adipose tissue increases by approximately 8.2% per year in the two years preceding the final menstrual period, and lean mass shifts from +0.2% per year before the transition to −0.2% per year during it. That lean-mass reversal drives the metabolic slowdown that makes standard calorie-cutting ineffective. Less muscle lowers resting metabolic rate, so the same deficit produces less fat loss and more regain.
Does Menopause Weight Gain Go Away On Its Own? No. It does not resolve without targeted action. The hormonal and body-composition changes driving it are progressive and ongoing.
Can High Cortisol Levels Contribute To Weight Gain During Menopause? Yes. Chronic stress and poor sleep raise cortisol, which promotes abdominal fat storage and accelerates muscle breakdown. These changes compound the estrogen-driven shifts already underway.
Standard calorie-cutting and cardio-only approaches backfire in this context because they accelerate the muscle loss that is already occurring. They further slow resting metabolic rate and make regain more likely. The 2026 VA/DoD Menopause Clinical Practice Guideline treats perimenopause as a distinct clinical phase with its own management module, separate from menopause management. As noted throughout this guide, the same guideline finds insufficient evidence to endorse any single dietary pattern and emphasizes individualized, evidence-based, patient-centered care. The right weight loss retreat for perimenopause weight gain must therefore address resistance training, protein adequacy, cortisol and sleep, and body-composition tracking, rather than focusing solely on the scale.

For a deeper look at one of these factors, PFC's guide on menopause stress and weight gain explores the cortisol-belly fat connection in detail and serves here as one criterion among seven for evaluating any retreat.
Talk with a perimenopause-focused coach.
A program that genuinely addresses perimenopause weight gain should meet all of the following criteria. Partial coverage rarely delivers lasting change.
PFC's complete guide to menopause weight loss programs covers each of these components in detail for readers who want a deeper look at program design.

Review your retreat options with PFC.
Three distinct program types dominate this category. Each serves a different need, and each fits a specific type of guest. PFC's guide on weight loss resorts versus wellness spas covers the two-category comparison. This section adds a third category and applies a perimenopause-specific lens.
To help you compare, the table below summarizes key differences among the three program types.
| Program Type | Typical Length | Primary Focus | Training Intensity | Diagnostics | Body-Composition Tracking | Ideal For |
|---|---|---|---|---|---|---|
| Clinical Medical Resort | 3–5 days | Testing, consultations, education | Light to moderate | Extensive labs and imaging | Varies by program | Women wanting diagnostics and expert input |
| Boutique Menopause Retreat | 5–7 days | Education, community, restoration | Light movement, yoga | Limited or none | Minimal, often scale only | Women seeking connection and learning |
| Structured Fitness Camp | 2–6+ weeks | Daily training, skills, habit change | Moderate to high, fully coached | Basic health screening | Regular, multi-point tracking | Women ready for measurable body change |
Clinical Medical Resort. Canyon Ranch's M/Power retreat in Lenox, Massachusetts, offers DEXA scans, comprehensive blood work and hormone panels, and one-on-one consultations with physicians, exercise physiologists, nutritionists, and licensed mental health professionals across a four-day program. This format suits women who want diagnostics, expert consultation, and a structured educational experience in a short window. Four days, however, do not provide enough time to build the habits, fitness base, or metabolic shift that perimenopause weight gain requires.
Boutique Menopause Retreat. Midlyfe Retreats' weeklong program at Sansara Resort in Cambutal, Panama, starts at $3,400 per person for double occupancy and includes workshops on hormones, bone and muscle health, nutrition, sleep, stress, and the pelvic floor. The educational content is relevant and the community experience is meaningful. However, in a group setting it is impossible to tailor content to any one person, and attendees left with handouts rather than a personalized action plan. This format fits women seeking education and community in a short, restorative format.
Structured Fitness Camp. This format provides immersive daily training, nutrition education, behavioral health support, and body-composition tracking across multiple weeks. Unite Fitness Retreat in Utah is one comparison point in this category, located in a downtown Salt Lake City hotel with clients accessing additional amenities off-site.
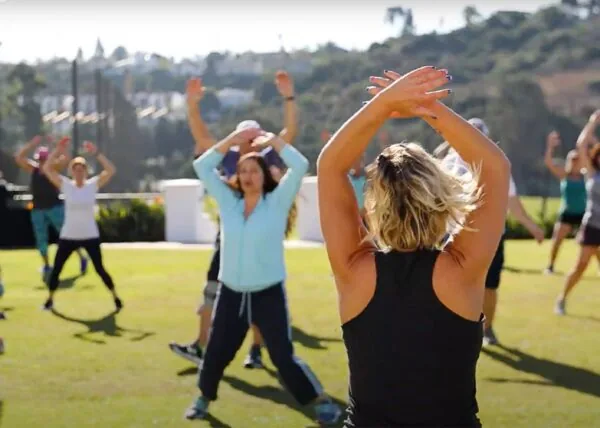
PFC is the structured fitness-camp option with resort-level amenities, operating at the Omni La Costa Resort & Spa in Carlsbad, California. The program includes 4–5 hours of daily training Monday through Friday and a 3–4:1 client-to-trainer ratio. Registered dietitians and licensed psychologists are on staff. A 17-point weekly report card tracks weight, body fat, eight circumference measurements, blood pressure, mile time, plank hold, push-ups, and key blood markers including LDL, HDL, triglycerides, and glucose. All facilities, meals, and programming are on-site, so nothing requires a van ride or off-site logistics.

A case study conducted in partnership with the University of California, San Diego (UCSD) found that 94% of client weight loss at PFC was purely fat, with lean muscle preserved or increased, far better than the typical 60/40 fat-to-muscle ratio of standard dieting. That finding directly addresses the muscle-and-metabolism problem at the center of perimenopause weight gain. Bone volume and strength were also maintained, which is particularly relevant for women in the perimenopausal transition.
Schedule your perimenopause-focused consultation.
Several program features actively work against perimenopause weight loss and can leave you worse off than when you arrived.
Before booking, ask for sample menus, staff credentials by name, and aftercare documentation in writing. A program that cannot produce these materials reveals important limits in its capabilities.
Hormone therapy and anti-obesity medications are legitimate conversations to have with a clinician. Hormone therapy attenuates the postmenopausal increase in abdominal and visceral fat regardless of initiation timing, but the benefits are lost on discontinuation. It is not indicated as a weight loss drug, yet it may improve body composition and sleep, which indirectly supports weight management. As noted earlier, the 2026 VA/DoD guideline finds insufficient evidence for any specific dietary approach and emphasizes individualized care.
GLP-1 medications work best in the context of resistance training, adequate protein, and addressing sleep. Without these supports, some of the weight lost may come from lean mass rather than fat, leaving a less favorable body composition even at a lower scale weight. PFC welcomes clients on GLP-1 medications and adjusts protocols to prioritize resistance training and protein, the two levers that determine how much muscle is preserved during rapid weight loss.
A weight loss retreat for perimenopause weight gain should complement medical care. Clients should consult their healthcare provider about hormone therapy and medication options before, during, and after any residential program.
The muscle built during a structured program is the asset that keeps weight off. Lean mass protects resting metabolic rate, which underpins sustainable maintenance. Without a structured transition, the metabolic gains from even an excellent program erode within weeks.
Practical aftercare guidance for the first 30 days includes the following priorities.
PFC's post-camp support includes virtual coaching, personalized meal plans, fitness programming, and ongoing communication with staff. Clients can email their trainers after leaving, which creates continuity that most programs do not offer and directly addresses the aftercare gap that often determines whether results last.
Plan your first 30 days home with PFC.
The decision framework in this guide reduces to seven criteria: resistance training, protein adequacy, cortisol and sleep management, body-composition tracking, menopause-literate staff, honest medical oversight, and structured aftercare. A program that meets all seven functions as a genuine perimenopause program. A program that meets only a few, even with a compelling brochure, operates more as a general wellness retreat with hormone-themed marketing.
The recommended next steps are straightforward. Consult a healthcare provider about hormone therapy and medication options. Compare multiple programs using the six questions above. Ask for sample menus, staff credentials, and aftercare documentation before booking any menopause weight loss retreat.
PFC is a leading luxury fitness and weight loss camp for adults, with 1,200+ reviews, a 90%+ five-star rating, and a UCSD case study showing that 94% of weight loss was fat with lean muscle preserved or increased. The program operates at the Omni La Costa Resort & Spa in Carlsbad, California, with registered dietitians, licensed psychologists, a 3–4:1 client-to-trainer ratio, and a 17-point weekly report card. For women past the transition, PFC's guide to wellness retreats for postmenopausal women covers how program priorities shift after the final menstrual period.
To discuss your goals and learn how PFC's program addresses the specific metabolic challenges of perimenopause, call (888) 488-8936 or use the consultation link below.
Start your personalized PFC consultation.
Perimenopause weight gain does not behave like a fixed or irreversible outcome, yet it also does not resolve on its own. The hormonal and metabolic changes driving it, including declining estrogen, rising cortisol, worsening insulin resistance, and accelerating muscle loss, are real and progressive. A structured program that prioritizes resistance training, adequate protein, cortisol management, and body-composition tracking can meaningfully change that trajectory. The key distinction is that the program must address the muscle-and-metabolism problem directly, not simply create a calorie deficit. The UCSD case study at PFC, described earlier, showed a 94% fat-loss outcome with lean muscle preserved or increased, which matters most for long-term metabolic health in this population.
The term "medically supervised" covers a wide range of actual oversight, from a one-time intake questionnaire to a clinician who reviews labs, medications, and symptoms on an ongoing basis. A structured fitness camp like PFC does not replace medical care, yet it provides something most clinical programs lack: immersive daily training, nutrition education, behavioral health support, and body-composition tracking across multiple weeks. PFC includes registered dietitians, licensed psychologists, and trainers with bachelor's and master's degrees, all operating within a structured program. Clients on GLP-1 medications or hormone therapy are welcomed, and protocols are adjusted accordingly. The two approaches work best together, with a retreat addressing lifestyle, behavioral, and fitness dimensions that clinical care alone cannot replicate.
Results vary based on starting weight, hormonal status, medications, and individual biology. For a typical client in her late 40s to mid-50s with 40–70 pounds to lose, PFC clients average 3–4 pounds of fat loss per week. More important than the scale number is the body-composition outcome. The UCSD case study mentioned earlier found that 94% of weight lost was fat, compared with the roughly 60/40 fat-to-muscle ratio typical of standard dieting. Clients also see improvements across 17 tracked data points, including blood pressure, cholesterol, glucose, mile time, strength, and circumference measurements. Bone volume and strength were also maintained in the case study, which is particularly relevant for perimenopausal women.
Yes. PFC welcomes clients on hormone therapy, GLP-1 medications such as semaglutide or tirzepatide, and other prescribed treatments. The program does not require clients to stop any medication, and staff adjust protocols based on each client's health profile. For clients on GLP-1 medications specifically, PFC emphasizes resistance training and protein adequacy, the two factors that determine how much muscle is preserved during rapid weight loss. Clients on hormone therapy benefit from the same resistance-training and body-composition focus. In all cases, PFC's program complements ongoing medical care, and clients are encouraged to remain in communication with their prescribing clinician throughout their stay.
Aftercare strongly predicts whether results from any intensive program last. PFC's post-camp support includes virtual coaching, personalized meal plans, fitness programming, and ongoing communication with staff, and clients can email their trainers after leaving. This continuity matters specifically for perimenopause because the hormonal and metabolic environment at home matches the one that drove the original weight gain. Without a structured transition, the habits, protein targets, and resistance-training frequency built during the program erode quickly. PFC's aftercare is designed to bridge the gap between the structured camp environment and sustainable independent practice, providing accountability and expert access beyond checkout.