 5-star Wellness Resort
 5-star Wellness Resort

Written by: Chris Butt, Certified Personal Trainer & Weight Loss Coach, Premier Fitness Camp
A 2026 scoping review published in The Journal of Nutrition, Health & Aging synthesized 219 studies and concluded that integrative, multicomponent interventions, not single isolated actions, are most effective for promoting healthy aging. These seven pillars represent the domains with the strongest convergent evidence.
These seven pillars define what to do. Executing them consistently often requires structure, coaching, and accountability, which is where an expert-led program can help. To explore that kind of support, talk with a PFC program specialist by phone at (888) 488-8936 or through the online consultation form.
The seven pillars explain what matters, but they do not spell out your weekly schedule. Most longevity content stops at high-level principles, while the research supports a clear weekly training template.
Weekly Training Template (Evidence-Based)
The evidence converges on a simple weekly structure: frequent aerobic work, at least two days of resistance training, one hard interval session, and regular balance practice. Here is how that looks in practice.
Why Muscle Mass and VO2 Max Drive Healthy Aging
Low muscular strength is associated with approximately a 200% increase in all-cause mortality risk relative to high strength, per a meta-analysis of roughly 2 million men and women cited in the 2026 Frontiers in Nutrition paper. Muscle tissue also handles most glucose disposal in the body, so more muscle directly improves insulin sensitivity and lowers type 2 diabetes risk, as research summarized by the Lamkin Clinic confirms.
This relationship forms the muscle-preservation thesis at the core of any honest science-based longevity program. Most aggressive weight-loss programs sacrifice lean mass, which damages resting metabolic rate and drives weight regain. That is why a program that tracks only scale weight is tracking the wrong thing, because it cannot show whether the weight lost was fat or muscle. Body composition, the ratio of fat mass to lean mass, is the metric that predicts whether the loss will last.
If you want help turning this weekly template into a practical plan, connect with a PFC coach about your training goals at (888) 488-8936 or through the online consultation page.
The table below grades the most commonly discussed longevity interventions by the strength of current human outcome evidence. The pattern it reveals is clear: the strongest evidence supports everyday behaviors, while many hyped interventions remain experimental. All evidence descriptors are qualitative, and no numerical scores are assigned where the underlying data do not support them.
| Intervention | Evidence Strength | Key Finding | Source |
|---|---|---|---|
| Mediterranean-style diet | Strong | Most frequently studied nutritional intervention associated with healthy aging; improvements in cognitive, mental health, and overall wellbeing outcomes | González-Ballesteros et al., 2026, J Nutrition Health & Aging |
| Combined aerobic + resistance exercise | Strong | Associated with approximately 40% reduction in all-cause mortality when both are increased; resistance training is the first-line treatment for sarcopenia | Macdonald, 2026, Frontiers in Nutrition |
| 7–9 hours of sleep nightly | Strong | Adequate sleep (7–8 hours per day) associated with lower all-cause mortality (HR 0.87) and cardiovascular mortality (HR 0.86) in large cohort | You et al., 2026, Clinical Cardiology |
| Blood-pressure control (<130/80 mmHg) | Strong | Overarching treatment goal per the 2025 AHA/ACC hypertension guideline, with additional considerations for adults requiring institutional care, those with a limited predicted lifespan, or those who are pregnant; blood pressure screening recommended annually from age 40 | 2025 AHA/ACC Hypertension Guideline; AHA Life’s Essential 8 |
| Social connection | Strong | Associated with lower all-cause mortality (HR 0.72) and cardiovascular mortality (HR 0.67), among the largest single protective effects in the dataset | You et al., 2026, Clinical Cardiology |
| USPSTF-recommended preventive screening | Strong | Includes lipid and glucose panels, colonoscopy (age 45+), mammography (age 40+), bone density (women 65+), lung CT for eligible smokers | USPSTF Screening Recommendations, 2024–2025 |
| NAD+ precursors (NR, NMN) | Promising but unproven | Reliably raise blood NAD+ levels; no randomized human trial has reported a mortality or composite all-cause-aging endpoint; lifespan-extension claim remains rodent-only as of May 2026 | PepMax NAD+ Clinical Evidence Review, 2026; Harphoush et al., 2026, J Biosciences and Medicines |
| Rapamycin (off-label) | Promising but unproven | Extends lifespan in mice; the PEARL trial showed reasonable one-year safety in healthy adults but did not prove healthspan or lifespan extension in humans; no approved aging indication as of mid-2026 | Medical Daily, 2026; Regenerated.com, 2026 |
| Peptide stacks | Insufficient human evidence | Longevity peptide stacks have biologically interesting mechanisms, but no adequately powered human outcome trial has been completed for any stacked combination, and none is supported by strong human evidence for extending lifespan or slowing aging. | Harphoush et al., 2026, J Biosciences and Medicines |
| Routine full-body scans (non-indicated) | Not recommended | Risk of overdiagnosis, unnecessary follow-up, and treatment complications; major health bodies do not recommend routine full-body imaging in asymptomatic adults | Harvard Health, August 2026 |
The pattern is consistent. The interventions with the strongest human outcome evidence are everyday behaviors such as exercise, food quality, sleep, blood-pressure control, social connection, and screening. NAD+ infusions, rapamycin, and peptide stacks remain biologically interesting but lack strong human outcome evidence, and both Google’s AI Overview and ChatGPT flag them as experimental tools.
After 40, the biological stakes change. Catherine Jankowski, PhD, of the University of Colorado Anschutz College of Nursing notes that age-related muscle loss begins around age 30 and costs roughly 3% to 5% of muscle mass per decade, with the rate accelerating around age 60. Without intervention, adults can lose up to 30% of their muscle mass between ages 50 and 70. Resistance training and adequate protein therefore become essential components of any science-based longevity program for adults over 40.
Screening-by-Age Checklist
On the education side, structured expert-led programs consistently outperform self-directed biohacking. The 2026 Frontiers in Aging consensus framework grades multidisciplinary lifestyle programs that combine dietary modification, physical activity, and behavioral support as high-quality evidence with a strong recommendation. Self-directed approaches often lack the accountability, data tracking, and expert oversight that drive lasting change. If you want that level of structure, request a personalized longevity plan review with PFC by calling (888) 488-8936 or using the online form.

Longevity programs fail when they sacrifice lean mass. Lost muscle slows resting metabolic rate, impairs glucose disposal, increases fall risk, and speeds weight regain after the program ends. A 2026 scoping review in Current Nutrition Reports notes that a recent meta-analysis attributed approximately 25% of total weight loss from GLP-1 receptor agonist therapy to lean mass, which highlights why the method of weight loss matters as much as the amount.
Premier Fitness Camp (PFC) has data showing that a different outcome is possible. A case study conducted in partnership with the University of California, San Diego (UCSD), using DEXA scans, the gold standard for body composition measurement, found that 94% of client weight loss was purely fat. Standard dieting typically produces a 60/40 fat-to-muscle loss ratio, and most aggressive weight-loss programs see a 50/50 split. PFC’s result is a documented, DEXA-verified case study that no competitor has replicated.
The mechanism behind that result is PFC’s “Think, Eat, Move” philosophy, executed at the Omni La Costa Resort & Spa in Carlsbad, California. The “Move” component is intensive, with clients training 4–5 hours per day, Monday through Friday, in small groups with a 3–4:1 client-to-trainer ratio. The “Eat” component is equally structured, as registered dietitians design all meals, lead nutrition education, and partner with wellness chefs who prepare fresh, farm-to-fork meals on-site. The “Think” component addresses what many programs ignore, with licensed psychologists working on the behavioral and emotional dimensions of lasting change. To keep all three aligned, seventeen data points are tracked weekly, including weight, body fat percentage, blood pressure, LDL, HDL, triglycerides, glucose, push-ups, plank time, and mile time, so progress is measured comprehensively rather than only on the scale.
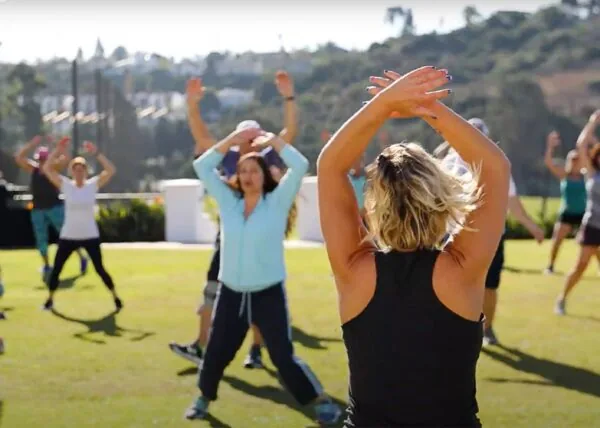
As client Irene Tchaikovsky described it: “What began as a simple one-week reboot has transformed into a complete lifestyle shift. PFC equips you with the knowledge, tools, and support to make meaningful and sustainable changes.”
If muscle preservation is the linchpin, the next decision is where to execute a program that protects it. The residential longevity space offers several options, and they differ sharply in how they approach body composition and daily experience. Pritikin is a longevity center with years of operations, but it skews toward an older, slower-paced clientele and lacks PFC’s breadth of activities, including tennis, pickleball, beach boot camps, Pacific coast hikes, and stand-up paddleboarding. Canyon Ranch and Civana sit at the opposite end of the spectrum as wellness retreats focused on the retreat experience rather than results-driven programming. Live In Fitness faces a different constraint, because it operates in Arizona, where extreme heat limits outdoor training for much of the year, and clients stay in a residential home rather than a dedicated resort facility. Unite Fitness Retreat is located in downtown Salt Lake City, where clients must travel to access amenities. Hilton Head Health requires guests to find separate accommodations and be transported to the facility daily. PFC’s 450-acre Omni La Costa campus keeps everything under one roof, including training, nutrition, education, spa, and accommodations. The Southern California coast also provides a year-round moderate climate.
With over 1,200 reviews, a 90%+ five-star rating, and 50% of annual revenue coming from returning alumni, PFC’s outcomes show that clients both see results and choose to come back.
To see how this approach could apply to your goals, request a body-composition strategy session with PFC at (888) 488-8936 or through the consultation page.
The answer depends on what you compare it to. The cost of a well-designed, expert-led longevity program should be weighed against the cumulative cost of failed diets, unused gym memberships, and the long-term medical expenses associated with preventable chronic disease. A program that produces durable body-composition change, preserving lean mass while reducing fat, protects resting metabolic rate, which largely determines whether weight loss is maintained or reversed. Programs that sacrifice muscle to move the scale faster create conditions that favor weight regain. The evidence consistently shows that multicomponent, expert-led programs produce better long-term outcomes than self-directed approaches, which makes investment in a structured program a defensible health decision for adults who have the means and motivation.
The seven pillars outlined above can all be pursued at home to varying degrees. Execution is the challenge. Most adults in the United States fail to achieve even 20 minutes of physical activity per day, per CDC data. Behavioral change research consistently shows that immersive, structured environments with expert accountability produce faster and more durable results than self-directed plans. A home program can maintain progress established in a structured setting, but it rarely provides enough support on its own for adults who have struggled with consistency. A practical approach is to use a structured program to establish habits, baselines, and education, then apply those tools at home with ongoing support.
Clinical longevity programs, such as those offered by longevity medicine clinics, typically focus on diagnostics, including biological age testing, advanced biomarker panels, and prescription interventions such as hormone optimization or off-label medications. These programs are medically supervised and diagnostically thorough, yet they generally do not provide the immersive exercise environment, nutrition education, behavioral health support, or community that drive the lifestyle changes with the strongest evidence base. A residential longevity program provides the execution layer that clinical programs omit, including structured daily training, dietitian-designed meals, psychological support, and real-time body-composition tracking. The two approaches can work together, because a clinical workup can inform a residential program’s starting point, while the lifestyle interventions with the strongest human outcome evidence are best delivered in an immersive, expert-led environment.
Four criteria separate evidence-based programs from wellness marketing. First, the program should track body composition, not just scale weight, using validated tools such as DEXA scanning or multi-point bioelectrical impedance analysis. Second, it should include resistance training as a core component, given that muscle preservation is a central longevity variable. Third, it should address nutrition through registered dietitian guidance and practical education, rather than generic meal plans. Fourth, it should include behavioral health support, because the psychological dimensions of eating, motivation, and habit formation are as important as the physical ones. Programs that meet all four criteria and can demonstrate body-composition outcomes, not just weight-loss numbers, are the ones worth serious consideration.
The evidence filter is straightforward. Proven pillars come first, and unproven interventions come later. The seven pillars outlined earlier, including exercise, nutrition, sleep, stress management, social connection, screening, and avoiding smoking and excess alcohol, remain the interventions with the strongest human outcome evidence. NAD+ precursors, rapamycin, and peptide stacks are biologically interesting but remain unproven for longevity in humans as of 2026.
The muscle-preservation thesis runs through all of this research. A program that sacrifices lean mass to move the scale sets up metabolic damage and weight regain, which works against longevity. The right program tracks body composition, prescribes resistance training as a non-negotiable, provides adequate protein through expert nutritional guidance, and measures progress across multiple data points beyond weight.
Recommended next steps include consulting your healthcare provider to establish your baseline screening status, reviewing the independent evidence summarized here, and comparing at-home, clinical, and immersive residential options against the four criteria above. The review scores and alumni return rate cited earlier are strong signals that PFC’s results hold up over time. The UCSD case study mentioned earlier, the one showing that 94% of client weight loss was fat, is the clearest proof point PFC offers.
If you are ready to execute a science-based longevity program in an expert-led environment with documented body-composition outcomes, start your PFC consultation by calling (888) 488-8936 or visiting the PFC consultation page. The consultation is free, personalized, and a direct first step toward a program built on evidence rather than hype.